Cellulitis
On this page
Cellulitis is a term used to describe an inflammation of the skin and subcutaneous tissues, typically due to infection by Streptococcus pyogenes or Staphylcoccus aureus.
Criteria for admission
NICE Clinical Knowledge Summaries recommend we use the Eron classification to guide how we manage patients with cellulitis:
They recommend the following that we admit for intravenous antibiotics the following patients:
The following is recommend regarding Eron Class II cellulitis:
Admission may not be necessary if the facilities and expertise are available in the community to give intravenous antibiotics and monitor the person - check local guidelines.
Other patients can be treated with oral antibiotics.
The BNF recommends flucloxacillin as first-line treatment for mild/moderate cellulitis. Clarithromycin or clindamycin is recommend in patients allergic to penicillin.
Many local protocols now suggest the use of oral clindamycin in patients who have failed to respond to flucloxacillin.
Severe cellulitis should be treated with intravenous benzylpenicillin + flucloxacillin.
Features
- commonly occurs on the shins
- erythema, pain, swelling
- there may be some associated systemic upset such as fever
Criteria for admission
NICE Clinical Knowledge Summaries recommend we use the Eron classification to guide how we manage patients with cellulitis:
| Class | Features |
|---|---|
| I | There are no signs of systemic toxicity and the person has no uncontrolled co-morbidities |
| II | The person is either systemically unwell or systemically well but with a co-morbidity (for example peripheral arterial disease, chronic venous insufficiency, or morbid obesity) which may complicate or delay resolution of infection |
| III | The person has significant systemic upset such as acute confusion, tachycardia, tachypnoea, hypotension, or unstable co-morbidities that may interfere with a response to treatment, or a limb-threatening infection due to vascular compromize |
| IV | The person has sepsis syndrome or a severe life-threatening infection such as necrotizing fasciitis |
They recommend the following that we admit for intravenous antibiotics the following patients:
- Has Eron Class III or Class IV cellulitis.
- Has severe or rapidly deteriorating cellulitis (for example extensive areas of skin).
- Is very young (under 1 year of age) or frail.
- Is immunocompromized.
- Has significant lymphoedema.
- Has facial cellulitis (unless very mild) or periorbital cellulitis.
The following is recommend regarding Eron Class II cellulitis:
Admission may not be necessary if the facilities and expertise are available in the community to give intravenous antibiotics and monitor the person - check local guidelines.
Other patients can be treated with oral antibiotics.
Management
The BNF recommends flucloxacillin as first-line treatment for mild/moderate cellulitis. Clarithromycin or clindamycin is recommend in patients allergic to penicillin.
Many local protocols now suggest the use of oral clindamycin in patients who have failed to respond to flucloxacillin.
Severe cellulitis should be treated with intravenous benzylpenicillin + flucloxacillin.
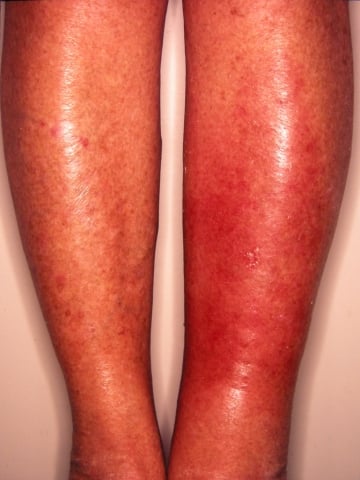 | |
| © Image used on license from DermNet NZ | |