Chickenpox
Chickenpox is caused by primary infection with varicella zoster virus. Shingles is reactivation of dormant virus in the dorsal root ganglia and other ganglia.
Chickenpox is highly infectious
If in doubt PCR is the most sensitive and specific test.
Chickenpox is highly infectious
- Spread primarily via the respiratory route
- Can be caught via direct contact with someone with chickenpox or shingles
- Infectivity = 24-48 hours before rash, until 5 days after the rash first appeared
- Incubation period = 10-21 days
- Chickenpox is predominantly a childhood illness. Incidence is highest before 10 years of age with over 90% of those aged ≥ 15 years positive for varicella IgG indicating immunity
Transmission is usually via respiratory droplets but can occur via contact with vesicle fluid. Incubation period is typically 10 to 14 days but may be up to 3 weeks.
Patients are at highest infectivity from 24-48 hours before the rash appears to 5 days after the rash starts (at which point the vesicles usually start to crust)
Patients are at highest infectivity from 24-48 hours before the rash appears to 5 days after the rash starts (at which point the vesicles usually start to crust)
Clinical features
- Fever initially
- Prodromal symptoms may include nausea, malaise, myalgia, anorexia, and headache
- Itchy, rash starting on head/trunk before spreading. Initially macular then papular then vesicular
- Systemic upset is usually mild
- Signs and symptoms tend to be more severe in older children/adults
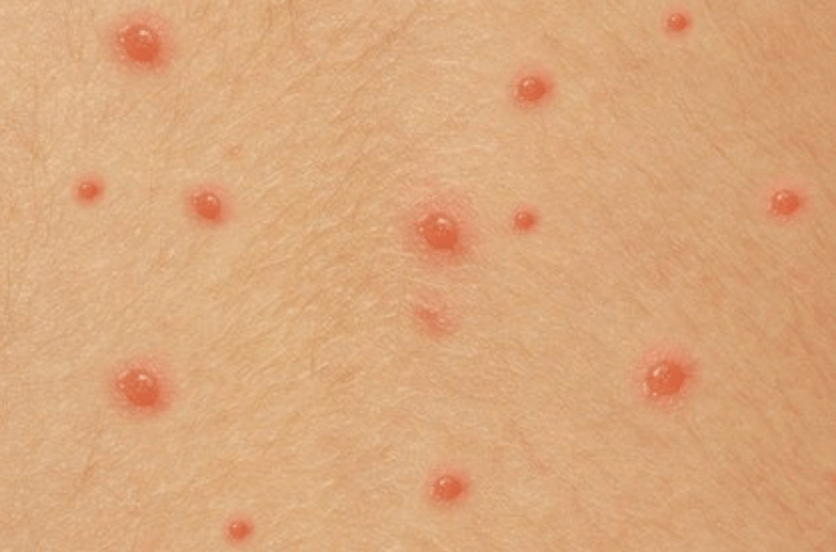 | |
Chickenpox rash typically progresses rapidly from macular to papular to vesicular lesions before crusting . Click on image to enlarge
Diagnosis
Diagnosis is almost always clinical.If in doubt PCR is the most sensitive and specific test.
Management
- Keep cool, trim nails
- Calamine lotion for itch
- Paracetamol for pain or fever if required
- Chlorphenamine for treating itch associated with chickenpox for people 1 year of age or older
- School exclusion: the 2016 Public Health England guidelines reverted to the traditional advice to exclude children until all vesicles have crusted over, rather than 5 days post onset of rash, which had been advocated over recent years
- Aciclovir is NOT recommended for otherwise healthy children with uncomplicated chickenpox but should be considered for an immunocompetent, non-pregnant adult or adolescent (aged 14 years or older) with chickenpox who presents within 24 hours of rash onset, particularly for people with severe chickenpox or those at increased risk of complications, such as smokers. The dose of oral aciclovir is 800 mg 5 times a day for 7 days.
- Aciclovir should also be considered for pregnant, breastfeeding, immunocompromised patients or neonates. It is advised to discuss prescribing with a specialist in these patient groups.
Complications:
Varicella is a self limiting illness for most but is should be noted that infection carries a higher risk for some groups including adults, pregnant women and immunocompromised patients. Of the mortality related to chickenpox in England and Wales, 80% occurs in adults.- Secondary bacterial infection of the lesions is not uncommon. Antibiotic therapy is indicated if this is the case.
- Pneumonia (most common significant complication in adults)
- Encephalitis (cerebellar involvement may be seen)
- Disseminated haemorrhagic chickenpox
- Arthritis, nephritis and pancreatitis may very rarely be seen
Chickenpox infection during pregnancy
Chickenpox infection during pregnancy can have complications for both the mother and fetus.
Complications for the mother:
Varicella in pregnancy is associated with increased likelihood of severe chickenpox. The mother is at increased risk of varicella pneumonia, hepatitis and encephalitis.
Complications for the fetus or neonate:
Varicella-zoster infection during the first 28 weeks of pregnancy can lead to intrauterine infection and fetal varicella syndrome. Fetal varicella syndrome consists of dermatomal scarring, eye defects, limb hypoplasia and neurological abnormalities
Incidence of fetal varicella syndrome varies depending on gestation:
Infection during the 4 weeks prior to delivery carries a risk of varicella infection of the newborn which may be severe i.e. disseminated or haemorrhagic varicella.
Chickenpox infection during pregnancy can have complications for both the mother and fetus.
Complications for the mother:
Varicella in pregnancy is associated with increased likelihood of severe chickenpox. The mother is at increased risk of varicella pneumonia, hepatitis and encephalitis.
- 10% of pregnant women with chickenpox develop pneumonia. Severity increases with later gestation.
- Case-fatality rate of pregnant women is estimated at 0–14%.
Complications for the fetus or neonate:
Varicella-zoster infection during the first 28 weeks of pregnancy can lead to intrauterine infection and fetal varicella syndrome. Fetal varicella syndrome consists of dermatomal scarring, eye defects, limb hypoplasia and neurological abnormalities
Incidence of fetal varicella syndrome varies depending on gestation:
- <1% in first 12 weeks
- 2% 13-20 weeks
- Very uncommon past 20 weeks but case reports have been documented
Infection during the 4 weeks prior to delivery carries a risk of varicella infection of the newborn which may be severe i.e. disseminated or haemorrhagic varicella.
Exposure to chickenpox
Post-exposure prophylaxis for varicella (chickenpox) is recommended for individuals at high risk of severe disease following significant exposure. This includes non-immune pregnant women, immunosuppressed individuals, and susceptible neonates. Varicella-zoster immunoglobulin (VZIG) is no longer the preferred prophylactic intervention in the UK. Since 2024 oral aciclovir (or valaciclovir) is the first choice of PEP for susceptible immunosuppressed individuals, all susceptible pregnant women at any stage of pregnancy and infants at high risk.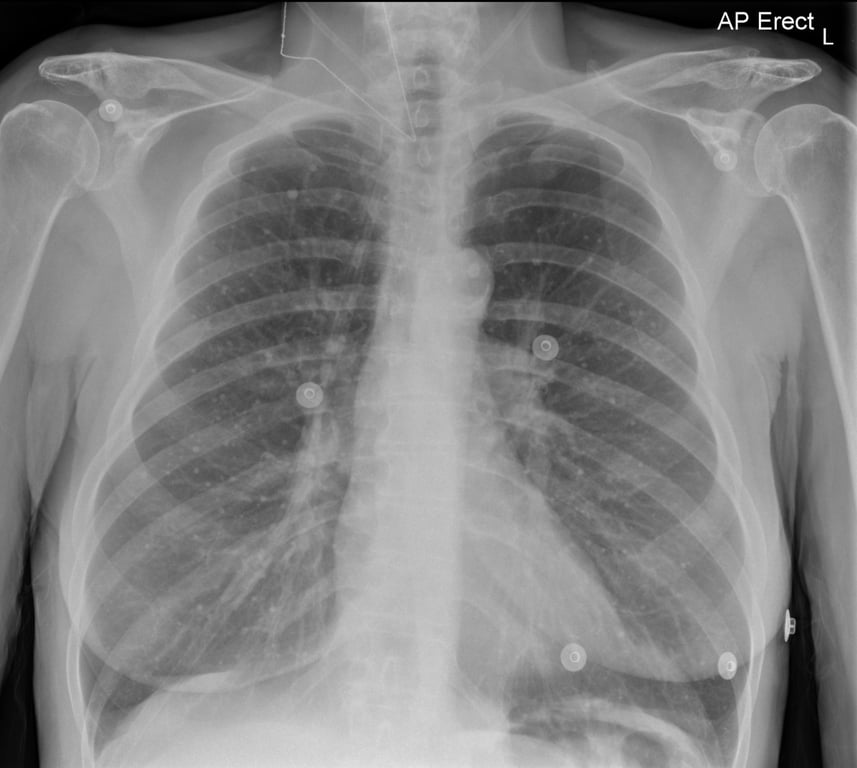 | |
| © Image used on license from Radiopaedia | |
Chest x-ray showing miliary opacities secondary to healed varicella pneumonia. Multiple tiny calcific miliary opacities noted throughout both lungs. These are of uniform size and density suggesting calcification. There is no focal lung parenchymal mass or cavitating lesion seen.The appearances are characteristic for healed varicella pneumonia.