Scaphoid fracture
Mechanism
- Typically fall onto outstretched hand with hyperextended wrist
Clinical features
- Anatomical snuffbox tenderness
- Pain on 'telescoping' thumb
- Scaphoid tubercle tenderness on palmar surface
Key Points
- May not be visible on X-ray initially.
- 2015 NICE guidance advocates MRI as 1st line imaging investigation due to the high rate of missed fractures on both X-ray & CT. Most emergency departments in the UK do not have sufficient access to MR scanning to facilitate this.
- High rate of AVN due to retrograde blood supply from dorsal carpal branch of radial artery.
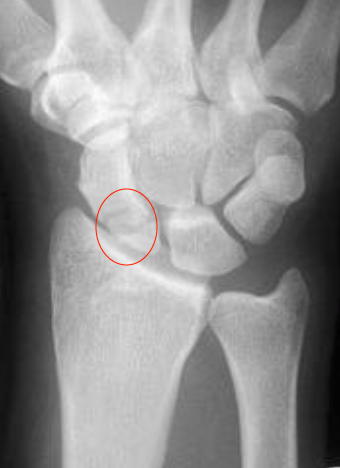 | |
Management
- Undisplaced fractures can be immobilised with thumb spica cast
- ORIF or screw fixation frequently required