Wolff-Parkinson White
Wolff-Parkinson White (WPW) syndrome is caused by a congenital accessory conducting pathway between the atria and ventricles leading to a atrioventricular re-entry tachycardia (AVRT). As the accessory pathway does not slow conduction AF can degenerate rapidly to VF
Possible ECG features include:
Differentiating between type A and type B**
Associations of WPW
Management
*in the majority of cases, or in a question without qualification, Wolff-Parkinson-White syndrome is associated with left axis deviation
**there is a rare type C WPW, WPW in which the delta waves are upright in leads V1-V4 but negative in leads V5-V6
***sotalol should be avoided if there is coexistent atrial fibrillation as prolonging the refractory period at the AV node may increase the rate of transmission through the accessory pathway, increasing the ventricular rate and potentially deteriorating into ventricular fibrillation
Possible ECG features include:
- short PR interval
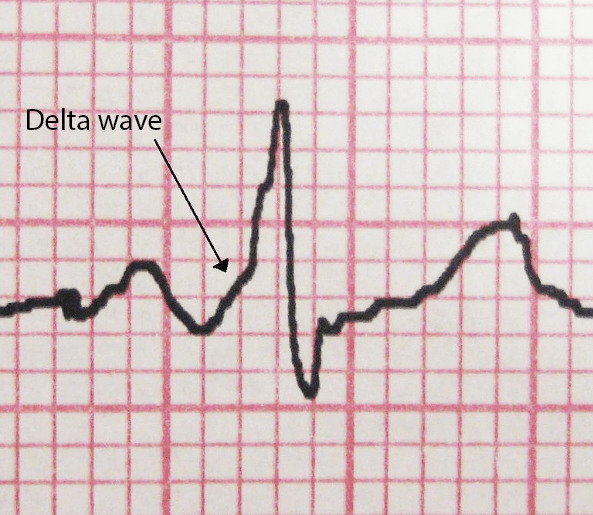
- wide QRS complexes with a slurred upstroke - 'delta wave'
- left axis deviation if right-sided accessory pathway*
- right axis deviation if left-sided accessory pathway*
 | |
| © Image used on license from Dr Smith, University of Minnesota | 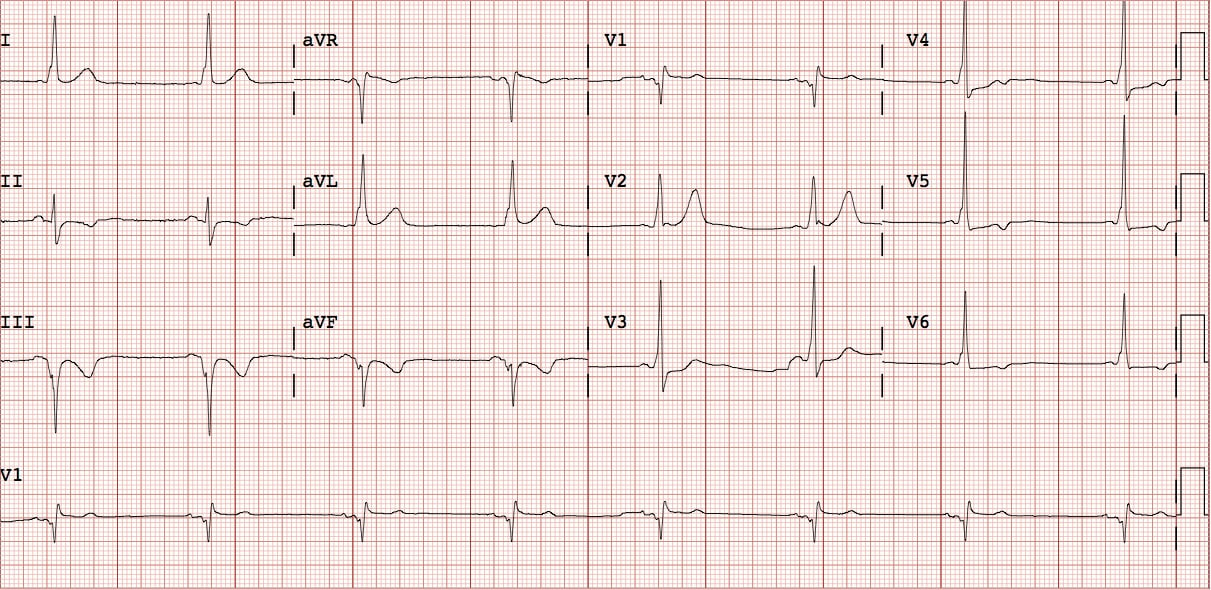 |
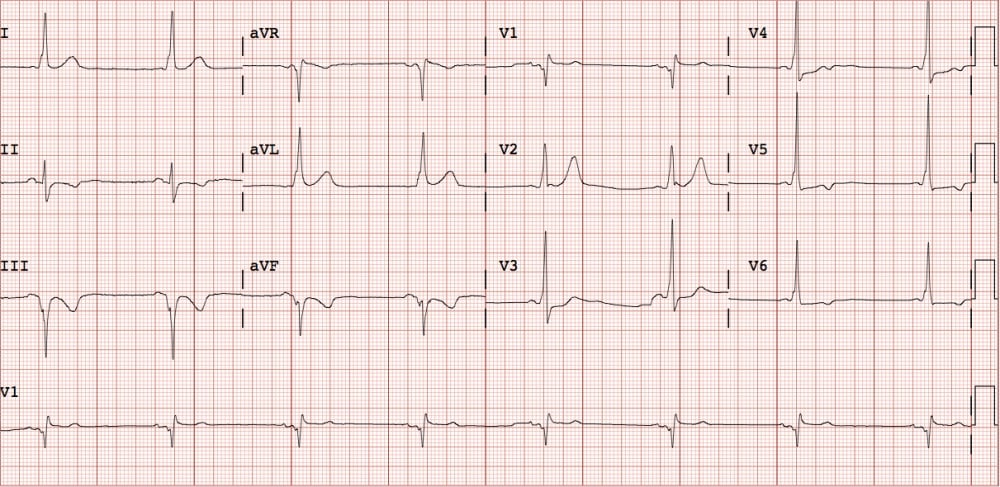
ECG showing short PR interval associated with a slurred upstroke (delta wave). Note the non-specific ST-T changes which are common in WPW and may be mistaken for ischaemia. The left axis deviation means that this is type B WPW, implying a right-sided pathway
 | |
| © Image used on license from Dr Smith, University of Minnesota | 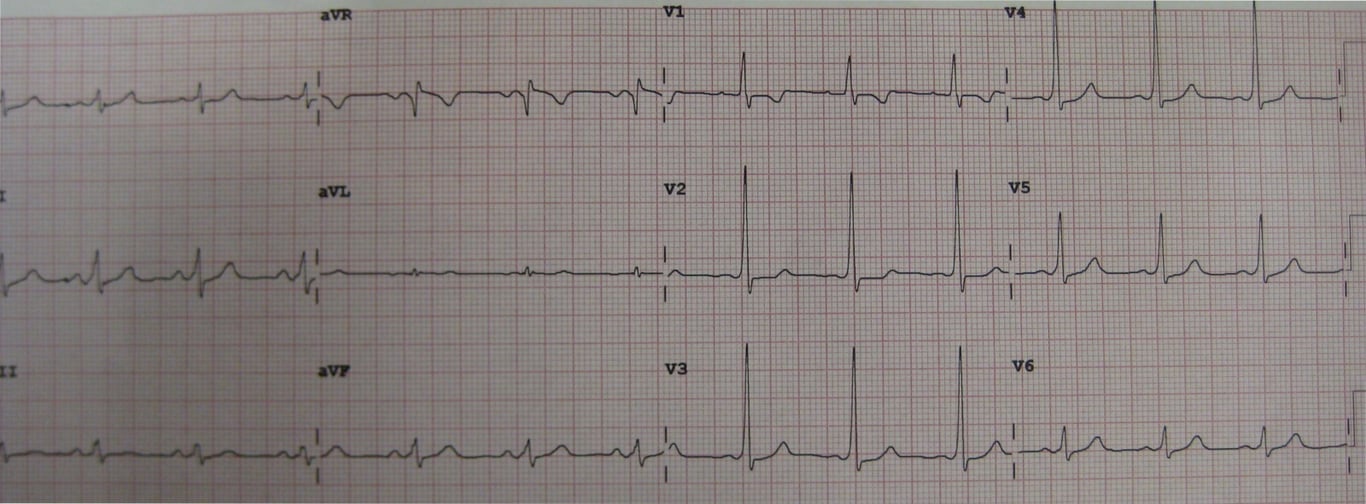 |
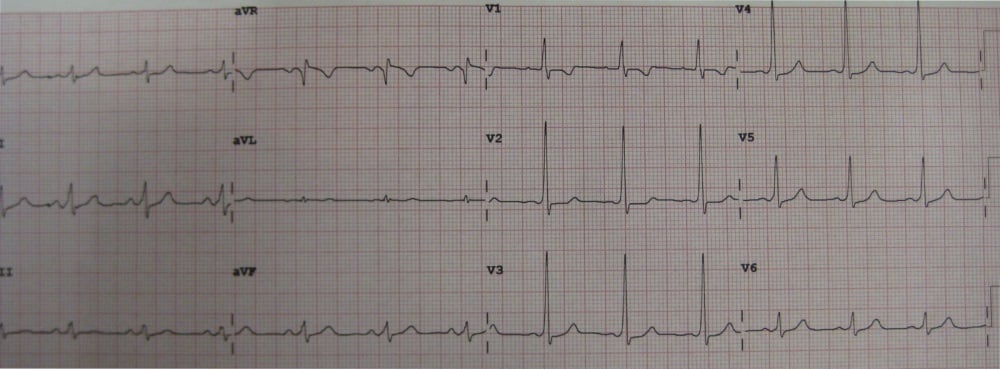
Further example showing a characteristic delta wave
Differentiating between type A and type B**
- type A (left-sided pathway): dominant R wave in V1
- type B (right-sided pathway): no dominant R wave in V1
 | |
Associations of WPW
- HOCM
- mitral valve prolapse
- Ebstein's anomaly
- thyrotoxicosis
- secundum ASD
Management
- definitive treatment: radiofrequency ablation of the accessory pathway
- medical therapy: sotalol***, amiodarone, flecainide
*in the majority of cases, or in a question without qualification, Wolff-Parkinson-White syndrome is associated with left axis deviation
**there is a rare type C WPW, WPW in which the delta waves are upright in leads V1-V4 but negative in leads V5-V6
***sotalol should be avoided if there is coexistent atrial fibrillation as prolonging the refractory period at the AV node may increase the rate of transmission through the accessory pathway, increasing the ventricular rate and potentially deteriorating into ventricular fibrillation