Pulmonary embolism: investigation
We know from experience that few patients (around 10%) present with the medical student textbook triad of pleuritic chest pain, dyspnoea and haemoptysis. Pulmonary embolism can be difficult to diagnose as it can present with virtually any cardiorespiratory symptom/sign depending on it's location and size.
So which features make pulmonary embolism more likely?
The PIOPED study1 in 2007 looked at the frequency of different symptoms and signs in patients who were diagnosed with pulmonary embolism.
The relative frequency of common clinical signs is shown below:
It is interesting to note that the Well's criteria for diagnosing a PE use tachycardia rather than tachypnoea.
2012 NICE guidelines
All patients with symptoms or signs suggestive of a PE should have a history taken, examination performed and a chest x-ray to exclude other pathology.
If a PE is still suspected a two-level PE Wells score should be performed:
Clinical probability simplified scores
If a PE is 'likely' (more than 4 points) arrange an immediate computed tomography pulmonary angiogram (CTPA). If there is a delay in getting the CTPA then give low-molecular weight heparin until the scan is performed.
If a PE is 'unlikely' (4 points or less) arranged a D-dimer test. If this is positive arrange an immediate computed tomography pulmonary angiogram (CTPA). If there is a delay in getting the CTPA then give low-molecular weight heparin until the scan is performed.
If the patient has an allergy to contrast media or renal impairment a V/Q scan should be used instead of a CTPA.
The consensus view from the British Thoracic Society and NICE guidelines is as follows:
Some other points
D-dimers
ECG
V/Q scan
CTPA
Pulmonary angiography
1. Clinical Characteristics of Patients with Acute Pulmonary Embolism(Data from PIOPED II) Am J Med. Oct 2007; 120(10): 871879.
So which features make pulmonary embolism more likely?
The PIOPED study1 in 2007 looked at the frequency of different symptoms and signs in patients who were diagnosed with pulmonary embolism.
The relative frequency of common clinical signs is shown below:
- Tachypnea (respiratory rate >16/min) - 96%
- Crackles - 58%
- Tachycardia (heart rate >100/min) - 44%
- Fever (temperature >37.8°C) - 43%
It is interesting to note that the Well's criteria for diagnosing a PE use tachycardia rather than tachypnoea.
2012 NICE guidelines
All patients with symptoms or signs suggestive of a PE should have a history taken, examination performed and a chest x-ray to exclude other pathology.
If a PE is still suspected a two-level PE Wells score should be performed:
| Clinical feature | Points |
|---|---|
| Clinical signs and symptoms of DVT (minimum of leg swelling and pain with palpation of the deep veins) | 3 |
| An alternative diagnosis is less likely than PE | 3 |
| Heart rate > 100 beats per minute | 1.5 |
| Immobilisation for more than 3 days or surgery in the previous 4 weeks | 1.5 |
| Previous DVT/PE | 1.5 |
| Haemoptysis | 1 |
| Malignancy (on treatment, treated in the last 6 months, or palliative) | 1 |
Clinical probability simplified scores
- PE likely - more than 4 points
- PE unlikely - 4 points or less
If a PE is 'likely' (more than 4 points) arrange an immediate computed tomography pulmonary angiogram (CTPA). If there is a delay in getting the CTPA then give low-molecular weight heparin until the scan is performed.
If a PE is 'unlikely' (4 points or less) arranged a D-dimer test. If this is positive arrange an immediate computed tomography pulmonary angiogram (CTPA). If there is a delay in getting the CTPA then give low-molecular weight heparin until the scan is performed.
If the patient has an allergy to contrast media or renal impairment a V/Q scan should be used instead of a CTPA.
CTPA or V/Q scan?
The consensus view from the British Thoracic Society and NICE guidelines is as follows:
- computed tomographic pulmonary angiography (CTPA) is now the recommended initial lung-imaging modality for non-massive PE. Advantages compared to V/Q scans include speed, easier to perform out-of-hours, a reduced need for further imaging and the possibility of providing an alternative diagnosis if PE is excluded
- if the CTPA is negative then patients do not need further investigations or treatment for PE
- ventilation-perfusion scanning may be used initially if appropriate facilities exist, the chest x-ray is normal, and there is no significant symptomatic concurrent cardiopulmonary disease
 | |
| © Image used on license from Radiopaedia | |
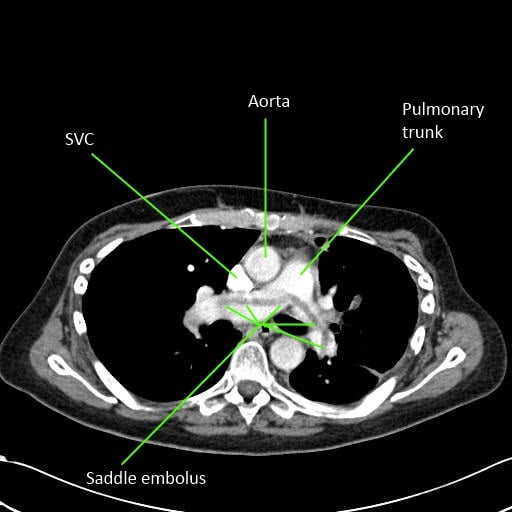
Labelled CTPA showing a large saddle embolus
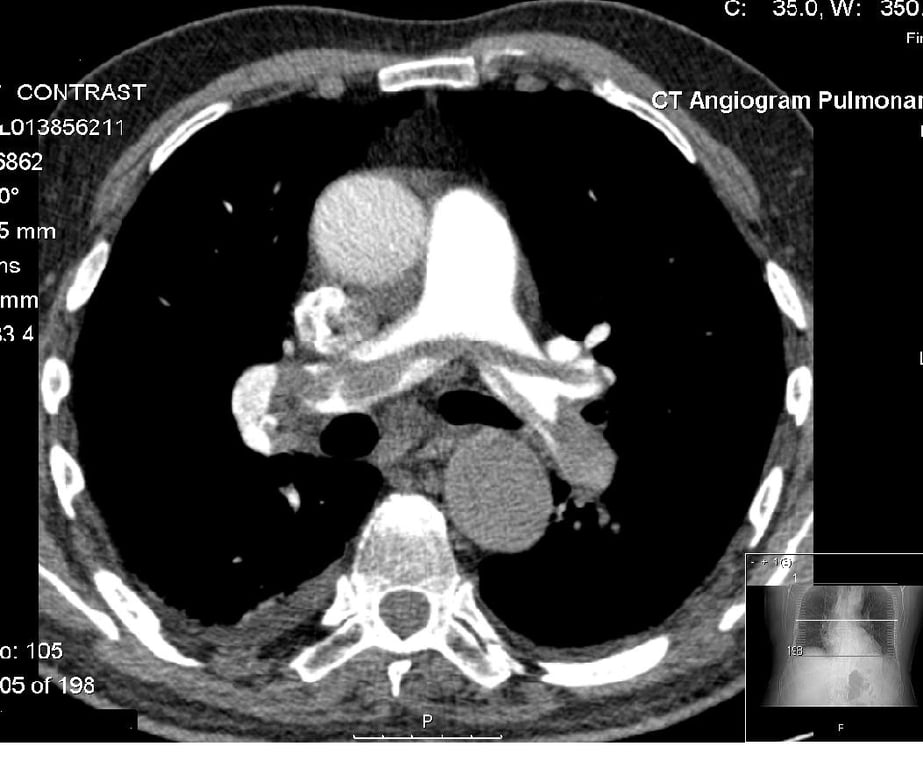 | |
Further CTPA again showing a saddle embolus
Some other points
D-dimers
- sensitivity = 95-98%, but poor specificity
ECG
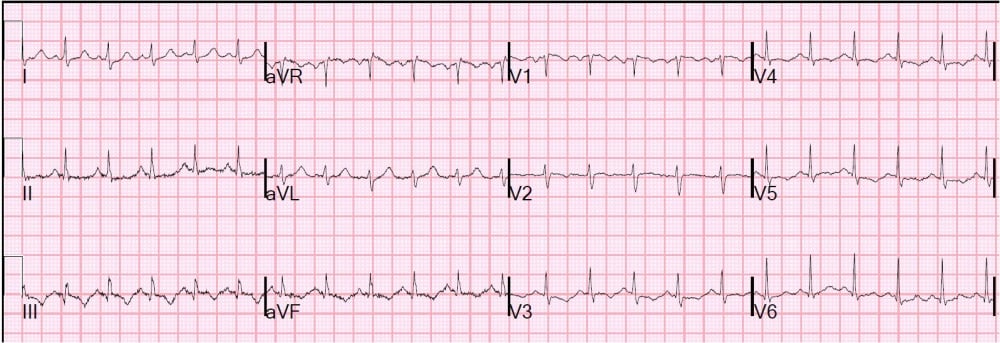
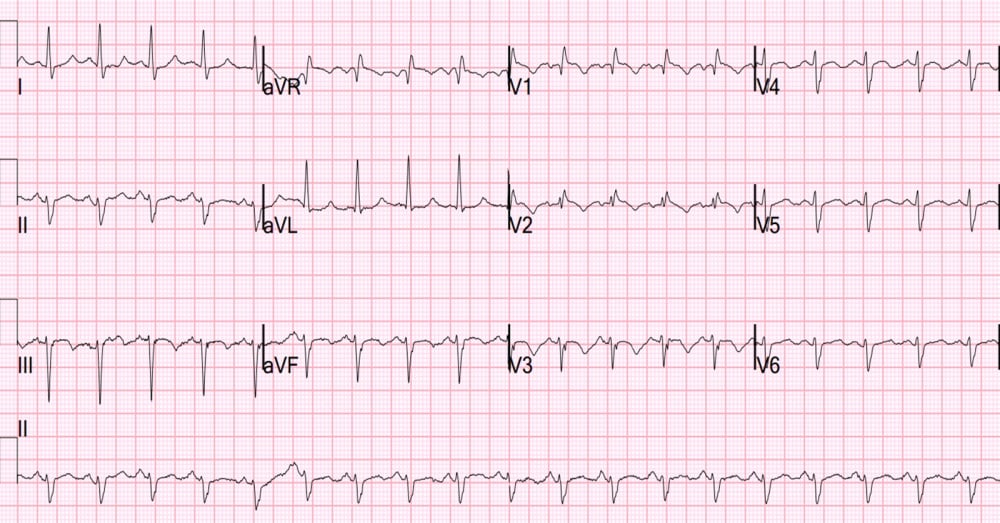
- the classic ECG changes seen in PE are a large S wave in lead I, a large Q wave in lead III and an inverted T wave in lead III - 'S1Q3T3'. However this change is seen in no more than 20% of patients
- right bundle branch block and right axis deviation are also associated with PE
- sinus tachycardia may also be seen
 | |
| © Image used on license from Dr Smith, University of Minnesota | 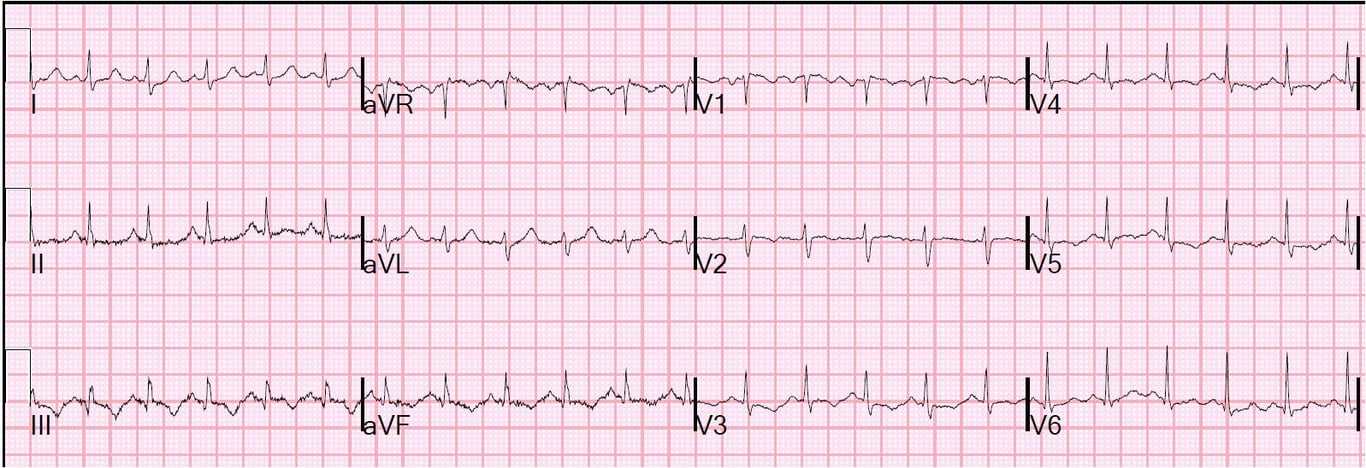 |
ECG from a patient with a PE. Shows a sinus tachycardia and a partial S1Q3T3 - the S wave is not particularly convincing.
 | |
| © Image used on license from Dr Smith, University of Minnesota | 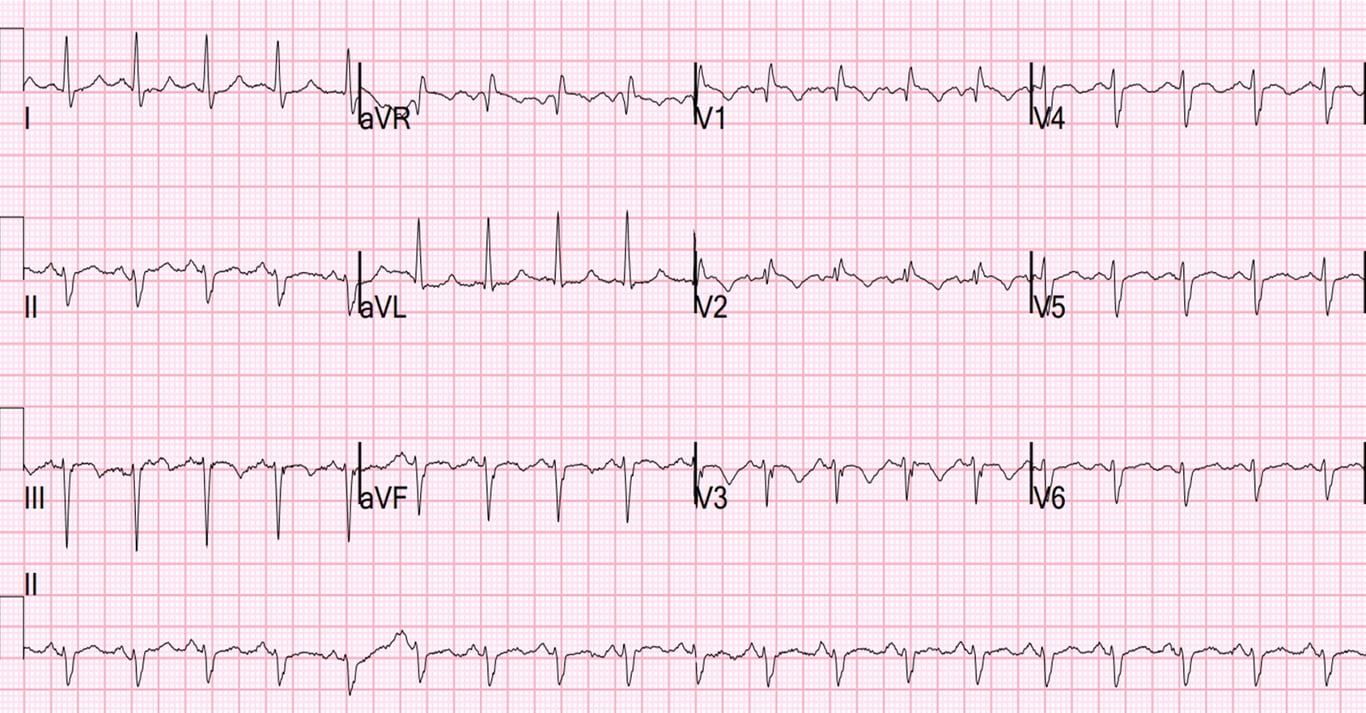 |
ECG of a patient with a PE. It shows some of the ECG features that may be associated with PE (sinus tachycardia, S1, T3 and T wave inversion in the precordial leads). Other features such as the left axis deviation are atypical.
V/Q scan
- sensitivity = 98%; specificity = 40% - high negative predictive value, i.e. if normal virtually excludes PE
- other causes of mismatch in V/Q include old pulmonary embolisms, AV malformations, vasculitis, previous radiotherapy
- COPD gives matched defects
CTPA
- peripheral emboli affecting subsegmental arteries may be missed
Pulmonary angiography
- the gold standard
- significant complication rate compared to other investigations
1. Clinical Characteristics of Patients with Acute Pulmonary Embolism(Data from PIOPED II) Am J Med. Oct 2007; 120(10): 871879.